


Another phrase to change. When there are problems in the bedroom, the expert recommends addressing them from “this is happening to me and I want to understand it,” not from “you no longer attract me.” STILL IMAGE: DTF St Louis frame (HBO Max).
FOR REFLECTION OUTSIDE THE BEDROOM
The usual thing is that a woman questions what is happening to her to feel less desire, however, the experts are clear: we must stop looking for defects and reflect on the new context.
By Cristina Martín Frutos
7 OCTOBER 2026 / 07:00
We have been told, loudly and clearly, that desire, as we age, is like energy: it does not disappear, it transforms. But the truth is that more than half of women in the menopausal transition report some change in their sex life. Especially in the desire to have intercourse. So, what happens? Is there a real problem behind it? Is it just in our imagination? Dr. Silvia P. González, gynecologist and president of the Spanish Association for the Study of Menopause, acknowledges that something happens, yes. However, she insists that it is not usually framed in the right way.

Join our menopause community
And you will be able to participate in events, contests and experiences, as well as receive all the information that will allow you to face this stage in the best possible way.
I want to join!
The gynecologist urges changing the approach. “We have to move from ‘what is happening to me that I have no desire?’ to ‘what would I need to have it?’ The first seeks a defect; the second, a condition. And almost always the answer has to do with rest, context, and non-sexualized affection. A different perspective that, in passing, raises the matter of hormones: they don’t seem to be to blame here as much as we suspected.
The context, the context is the context!
Of course, hormonal imbalances have a lot to say when talking about libido. The menopausal decline in estrogen can influence lubrication and the elasticity of the tissues. This, in turn, can lead to dryness and even dyspareunia (pain during intercourse). But these factors do not always exist. More, these aspects may cause sex not to be equated with penetration. However, they do not have to affect desire as such. “We are facing the only symptom in which all fronts converge. A hot flash is a thermoregulation phenomenon; desire, on the other hand, depends on hormones, yes. But it also depends on the brain, the state of the tissue, stress, mood, sleep, personal history, and the relationship. If one of those vectors goes awry, you will notice. And in perimenopause several vectors go awry at once,” explains Silvia P. González.
Therefore, in her view, “the context almost always weighs more than hormones.” Although hormones are responsible for setting the playing field. The doctor often uses a clarifying example to explain it: desire works like a car with an accelerator and a brake. “The hormones are mainly on the accelerator. But at this stage what is triggered are the brakes: insomnia; mental load; having teenage children and aging parents at the same time; a body that has changed and a culture that has taught us to look at it with suspicion. You can press the accelerator as much as you want, but if the handbrake is on, the car won’t move.
Is it my fault… or my partner’s?
The president of AEEM starts by wiping out guilt with one stroke. It is not a question of the woman or her partner. “Guilt appears because we have turned desire into a conjugal obligation and into a thermometer of love. And it is neither of those things,” she explains. In fact, she recalls that “the mismatch of desire between two people is the most common situation in stable couples, not the exception. There is no perfectly synchronized couple; there is a couple that talks about it.” In heterosexual couples, erectile dysfunction spikes around the fifties. If it is a relationship between two women, both may be in climacteric…
That is why it is so important to share it with the partner. That said, “you have to talk about it outside the bed and outside the moment of rejection.” In addition, the gynecologist recommends turning the issue around and proposing it from the “this is happening to me and I want to understand it” vantage point. Not from the idea of “you no longer attract me.” Finally, we must not forget that, when they reach 45 or 50 years old, many couples have been together for decades. And, out of habit, laziness, or routine, they do exactly the same thing. In the same order. The same days. At the same time. “That is not a hormonal problem; it is that routine and desire do not go well together,” the expert reminds us.
Adapting to the new desire
In this context, the idea is by no means to strive to recover the sexual life you had at 25. At that age there was urgency, hormones, discovery… But also haste, insecurity, and a reasonable lack of knowledge about one’s own body and emotions. Therefore, the ideal, according to Dr. González and the vast majority of experts, is to adapt to the new type of desire. For this, the gynecologist offers some pointers:
- More time. The genital response becomes slower; what previously took two minutes now takes ten or fifteen. It is not a failure, it is a rhythm.
- Lubricant always when needed, without drama. And if there is baseline dryness, a prescribed vaginal moisturizer, which is a different thing.
- Schedule. It sounds antiromantic, but it works: with receptive desire, opportunity precedes the desire. A colleague I greatly admire constantly talks about reserving time for your partner: one hour a day, one day a week, and a weekend once a month…
- Expand the repertoire, including erotic toys. A vibrator is not someone’s substitute; it is a facilitator.
- Decoitalize. If the entire encounter is organized around penetration and penetration is bothersome, the entire system blocks.
Other practical tools: from supplementation to mindfulness
The first thing to bear in mind is whether there is a physical cause that influences libido. Because, although desire can be altered by various factors, we must not forget that certain conditions — dryness, vulvovaginal atrophy, recurrent cystitis… — can provoke not that desire disappears, but that it retreats. “In these cases it is a perfectly logical protective mechanism. Nobody desires what hurts,” notes the doctor. Therefore it can and should be treated medically. With vaginal estrogens, evaluating hormone therapy, with testosterone under medical supervision, and, of course, physiotherapy.
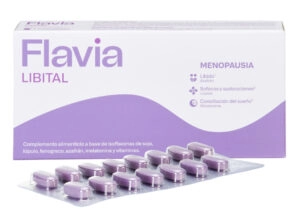
When we focus on libido as such, sex therapy and, especially, mindfulness programs applied to sexuality work. “They have clinical trials with notable results in desire and arousal. They address exactly what most blocks it: the disconnection between what the body registers and what the head is thinking while it happens,” assures the gynecologist. And what about supplementation? “It doesn’t work miracles, but there are some scientifically supported ingredients, such as saffron and fenugreek.”
The former contains crocins and safranal, which act on serotonin and dopamine —much milder than an antidepressant—, and in randomized trials have improved desire and satisfaction, even in women with antidepressant-associated sexual dysfunction. Fenugreek, in a placebo-controlled trial, increased free testosterone by about 24% and improved desire and arousal as a result. Both are found in Flavia Libital, formulated with those women in mind who have spent some time wondering what is happening to them. That said, from now on, they should think more about what they need to restore that desire…






